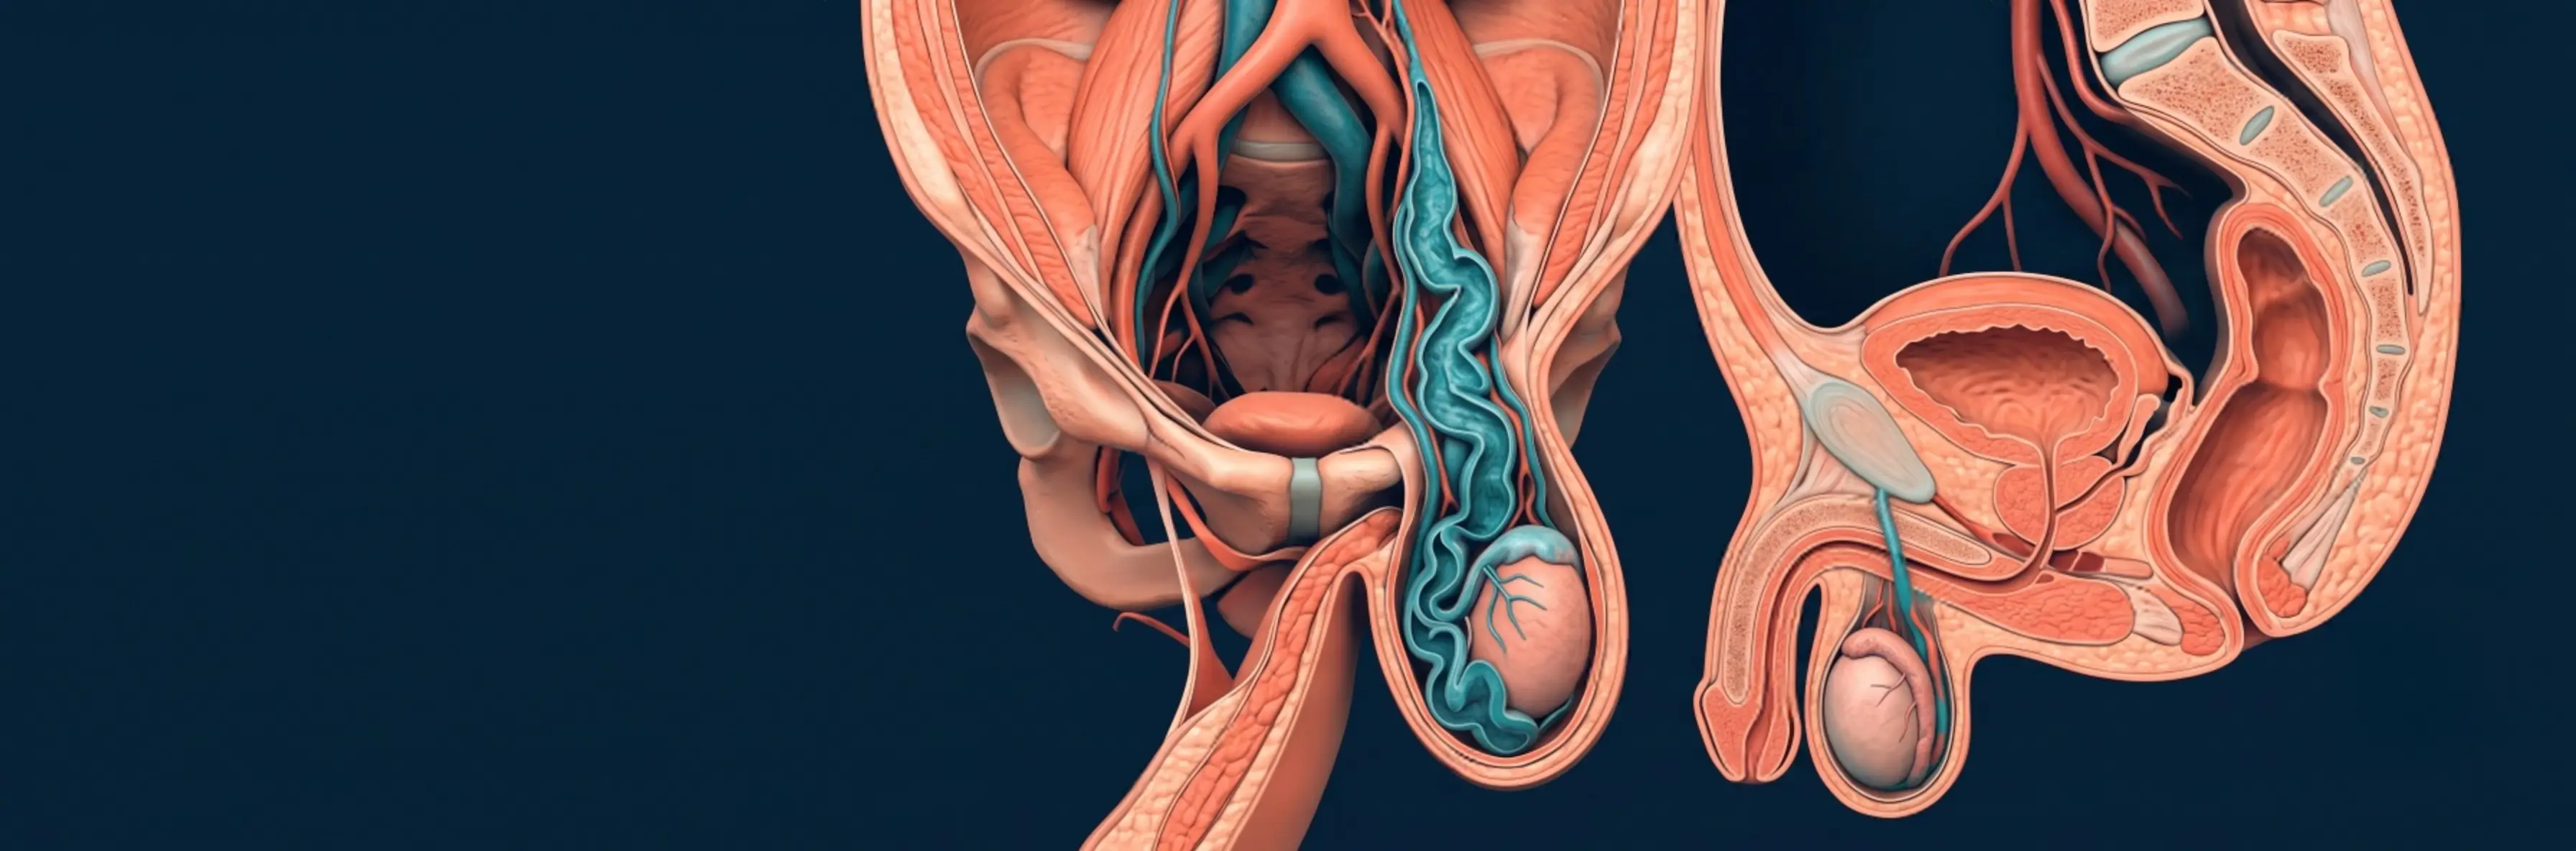
A varicocele is an enlarged vein inside the scrotum, similar to a varicose vein in the leg. It is the single most correctable cause of male infertility. And yet most men in their 30s with fertility problems have never been told to check for it.
What exactly is a varicocele?
The testes are supplied by a network of small veins called the pampiniform plexus. Normally, these veins have one-way valves that keep blood flowing upward toward the heart. When these valves fail, blood pools in the veins, causing them to dilate. This is a varicocele.
Varicoceles are found in about 15% of all adult men. In men being investigated for infertility, that number rises to 35–40%.
Why does a varicocele affect fertility?
The testes sit outside the body for a reason. They need to be 2–3°C cooler than core body temperature to produce healthy sperm. Pooled blood in a varicocele raises scrotal temperature. Over time, this heat damages sperm production in three specific ways:
- Low sperm count (oligospermia): fewer sperm are produced
- Poor motility: sperm that are produced move sluggishly
- Abnormal morphology: sperm shapes become irregular
A semen analysis will often show all three abnormalities together. This combination is sometimes called "varicocele pattern" and is a strong reason to investigate further.
Does every varicocele need treatment?
No. Many men with varicoceles have normal fertility and no symptoms. Treatment is recommended when all three of the following are present:
- The varicocele is detectable on physical examination or ultrasound
- The couple has a documented fertility problem
- The female partner's investigations are normal or have treatable findings
A varicocele found incidentally during a routine check, with no fertility concern and no pain, often requires only monitoring, not surgery.
Symptoms to watch for
Most varicoceles cause no symptoms at all and are discovered only during fertility investigations. When symptoms do appear, they include:
- A dull, dragging ache in the left testicle (varicoceles are left-sided in 90% of cases)
- Visible or palpable swollen veins in the scrotum, described as feeling like a "bag of worms"
- Discomfort that worsens after standing for long periods or physical exertion
- In severe or longstanding cases, one testicle smaller than the other (testicular atrophy)
How is a varicocele diagnosed?
Diagnosis is clinical first, a urologist examines the scrotum while the patient stands and performs a Valsalva manoeuvre (bearing down as if straining). Varicoceles are graded:
- Grade 1: Palpable only during Valsalva
- Grade 2: Palpable without Valsalva, not visible
- Grade 3: Visible through the skin
A scrotal Doppler ultrasound confirms the diagnosis, measures vein diameter, and detects reflux, reverse blood flow that confirms valve failure.
Treatment: microscopic varicocelectomy
The most effective treatment is microscopic varicocelectomy: a surgical procedure performed under a surgical microscope. Under magnification, the dilated veins are tied off while preserving the testicular artery and lymphatic vessels.
Why microscopic? Studies consistently show that microscopic varicocelectomy has higher success rates and fewer complications compared to open or laparoscopic approaches. The risk of hydrocele (fluid accumulation) after the procedure drops from 7–8% to under 1%.
At Urocare Hospital Gondia, this procedure is performed as a day-care surgery under spinal or general anaesthesia. Most men return to desk work within 3–5 days.
What results can you expect?
Semen parameters typically begin improving 3 months after surgery. This is the time required for a new generation of sperm to complete their development cycle. By 6 months, studies report:
- Sperm count improvement in 60–70% of men
- Natural pregnancy rates of 30–40% within one year
- Improved IVF/ICSI outcomes in men who proceed to assisted conception
The earlier varicocele repair is done, the better the results, progressive testicular damage accumulates over years.
A note on timing: If you and your partner have been trying to conceive for more than 12 months without success (or 6 months if she is over 35), both of you should be investigated simultaneously. Semen analysis is simple, non-invasive, and often the first investigation that gives a clear answer.
When to see a urologist in Gondia
Book a consultation if you notice any of the following:
- Persistent aching or heaviness in the scrotum
- One testicle significantly smaller than the other
- Difficulty conceiving after 12 months of trying
- A semen analysis that shows low count, low motility, or abnormal forms
Varicocele is not an emergency, but it is a time-sensitive problem. The longer heat stress continues, the more difficult the damage is to reverse.